Bloating in perimenopause usually has more than one thing behind it, and they need separating before anything helps. There is digestive bloating — gas, distension after eating, a bowel habit that has changed. There is fluid retention — puffiness, tight rings, sock marks, a heaviness that arrived without any change in diet or activity. And underneath both sits a metabolic shift, because oestrogen influences insulin sensitivity and where fat is stored. They feel similar from the inside. They are not the same problem, and they do not respond to the same thing.
Perimenopause is the years of fluctuating hormones before periods stop, and it often begins long before anyone names it. Most people arrive at this having already cut something out — bread, dairy, whatever the internet suggested — and having got nowhere.
Why does the same food suddenly behave differently?
Because oestrogen is not only a reproductive hormone. It influences insulin sensitivity, where fat is stored, how you build and hold muscle, bone turnover, and how blood vessels behave. As it becomes erratic and then falls, all of those shift at once — so an unchanged diet can produce a changed body without you doing anything differently.
The practical consequence is that midlife weight gain is a metabolic change rather than a failure of willpower, and it does not respond well to the tactic most people reach for. Eating considerably less while losing muscle makes the underlying problem worse, not better. Bloating sits in the same decade and tends to get the same treatment — cut something out, wait, be disappointed.
The gut side: clearance, not just digestion
Oestrogen has to be metabolised by the liver and removed via the gut, so constipation and a struggling liver keep it circulating no matter how good the rest of the plan is. That is the sentence most people have never been told, and it is why I treat bowel habit at this stage as part of the hormone picture rather than a separate complaint.
It would be fair to say that everyone with constipation and slow-moving stools has a leaky gut. That is a blunt thing to say, and I say it because bowel habit is the one people wave away. Around 90% of our hormones are produced at the gut wall — if it is not intact, you are going to have a hormonal problem.
I have written up the gut wall in full — what damages it, and what rebuilds it. The short version on the food side is two things: bone broth, which contains glutamine and brings collagen and highly absorbable vitamins and minerals with it, and cabbage, which is another source of glutamine. Alongside those, polyphenols and fibre, because they are the prebiotic food the bacteria that look after the gut membrane live on.
On probiotics, one I name often: Gut Health, by The Positive Science People. It is really good for reducing bloating, and very conveniently it has digestive enzymes in it as well. It is available from The Natural Dispensary and my discount code NCHA10 takes 10% off. Whatever you take, change the strains every three months rather than staying on one forever — different strains support different areas of the body.
The fluid side: puffiness is not the same as bloating
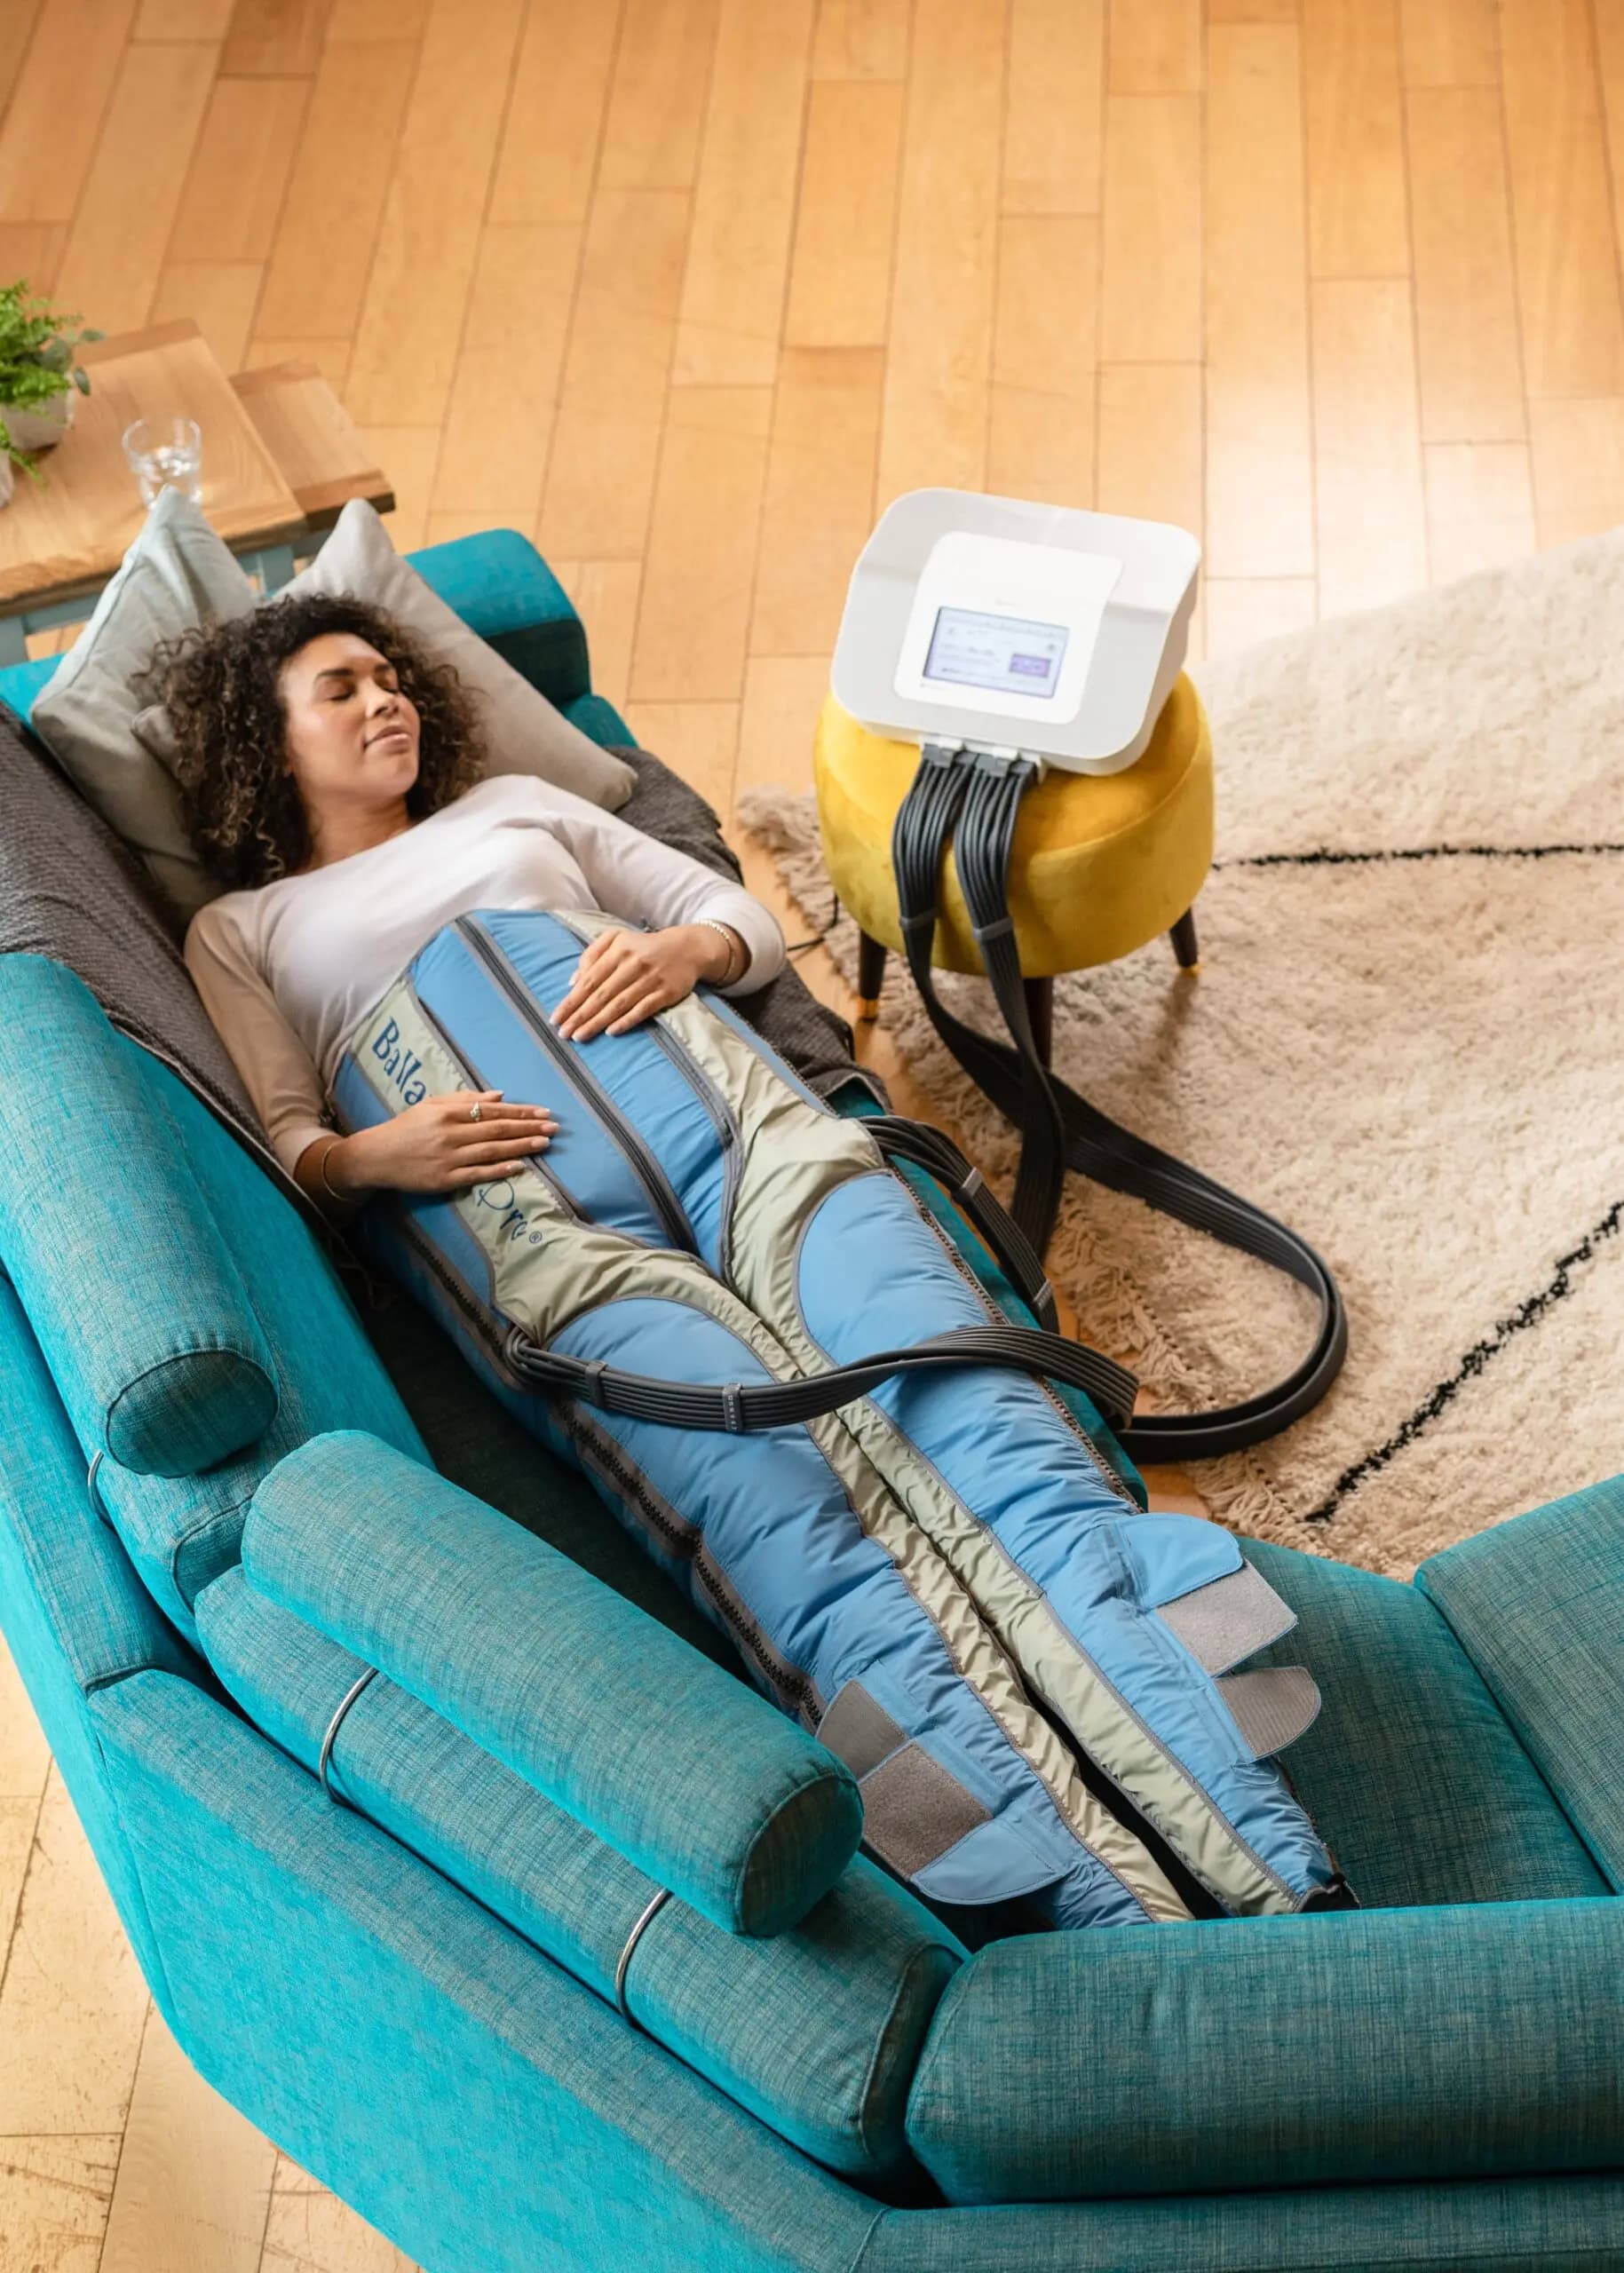
Fluid retention, puffiness and a heaviness that arrived without any change in diet or activity are one of the most common reasons women in perimenopause and menopause come to us — and that is a drainage problem rather than a digestive one. Your lymphatic system has no pump. It is propelled entirely by muscle contraction, movement and breath, so it moves when you do and slows when you do not.
Sluggish lymphatic flow rarely announces itself. It shows up as a collection of small things that are individually easy to live with:
- Bloating, particularly through the afternoon and evening
- Puffy skin, tight rings, sock marks, fluid retention
- Persistent fatigue that sleep does not seem to fix
- Brain fog
- Skin breakouts and dull skin tone
None of those are alarming on their own. That is the problem — they get absorbed into what you assume is just being in your forties. This is the layer a lymphatic compression session addresses directly, and it is why fluid retention and puffiness are on the list of things the Body Ballancer is used for. It is not a treatment for perimenopause and it does not claim to be. It moves fluid that is not moving on its own.
Blood sugar first, almost every time
Blood sugar stability is the fastest lever available and it underpins cortisol, which underpins everything else. Cortisol and progesterone are also made from shared raw materials, so a sustained stress load can reduce progesterone — and supporting progesterone alone is then working against something that is still being generated.
If you want somewhere concrete to start, the full-day reset lays out what a day built around stable blood sugar actually looks like, meal by meal. Insulin resistance is the longer read behind why it matters so much in this decade.
Protein and muscle — the part that gets skipped
Muscle is the most valuable asset in this decade and the easiest to lose. It is where glucose goes, it is what keeps your metabolic rate up, it is what protects your joints, and it is the strongest signal available for maintaining bone density. Losing it quietly through your forties and fifties is what makes the seventies difficult.
So protein requirements go up at exactly the point most people are eating less, and resistance training stops being optional. This is the single change we most often make, and it is usually the one with the largest effect on how someone feels a few months later.
Is there a test for this?
Not a single one that settles it. Blood hormone levels fluctuate so much during perimenopause that one reading tells you very little, which is why symptom mapping over time is more useful than a one-off panel. Where the question is how you are producing and clearing hormones, a comprehensive dried urine hormone panel gives us metabolites as well as levels, and that matters a great deal for oestrogen.
A full thyroid panel is often worth having alongside it — free T4, free T3, reverse T3 and antibodies, not only TSH, since a normal TSH is regularly the reason someone has been told there is nothing wrong. We test where it will change the plan, and we say so when it will not. Functional testing is where that conversation starts.
What to rule out first
If you have an active gut condition that needs investigating — H. pylori, parasites, significant dysbiosis, inflammatory bowel disease — that work comes before any of this. Fibre into an inflamed or infected gut is not a kindness.
And bloating that is new, persistent or getting worse belongs in front of your GP before it belongs in front of me. Nothing in this article is a reason to delay that appointment, and I would far rather you had it.
Hormone and thyroid symptoms rarely travel alone. A full consultation looks at the whole picture.
Book Consultation →Does this work alongside HRT?
Yes. HRT is a medical decision between you and your GP or menopause specialist, and we do not advise for or against it. Where you are taking it, nutrition works alongside it — HRT does not remove the need for protein, muscle, blood sugar stability, or a liver and gut that can clear hormones properly. Where it is not right for you, or not available to you, nutrition and lifestyle carry more of the load and the plan is built accordingly.
Common questions
How do I know if I am in perimenopause?
Usually by the pattern rather than a test. Blood hormone levels fluctuate so much during perimenopause that a single reading tells you very little, which is why symptom mapping over time is more useful than a one-off panel.
I am in my late thirties. Is it too early for this to be the reason?
No. Perimenopause commonly starts earlier than people expect, and going into it with good muscle mass, stable blood sugar and solid nutrient status is by far the best preparation available.
Should I just cut out gluten and dairy?
Most people have already tried it by the time they get to me, and if it had been the answer they would not be reading this. Cutting something out is worth doing deliberately, for a defined period, with something specific being looked for — done indefinitely and by guesswork, it narrows the diet without answering the question.
How long before I notice a difference?
Blood sugar and energy changes often show within two to three weeks. Cycle-related change realistically takes three months, because that is roughly how long the developing follicle takes — anyone promising faster is selling something.
The bottom line
Bloating in perimenopause is rarely one thing, and the reason it resists the obvious fixes is that the obvious fixes only ever address one layer at a time. Sort the bowel habit and the gut wall, because oestrogen leaves that way. Sort blood sugar, because it underpins the rest. Look separately at fluid, because puffiness is a drainage problem and responds to something different. Then keep the muscle, because that is the part that decides how the next twenty years go.
If that reads like your last two years, it is a longer conversation than a blog post can have. Perimenopause and menopause support is what a full consultation covers, and a free 15-minute call first is the sensible way to find out whether it is the right fit.
This article shares naturopathic and lifestyle guidance for general education and isn't a substitute for personalised medical advice. Always speak to your GP before changing any prescribed medication or if you have an existing health condition.